8 Weeks
15 mg Vial- VialsTesamorelin + Ipamorelin Blend mg vials
- 10
- U-100 Syringesone sterile syringe per dose
- 66
- BAC Water30 mL multi-dose vials
- 2
- Alcohol Padsvial stopper + skin prep
- 122
56 total doses over 8 weeks
Tesamorelin Acetate + Ipamorelin Blend
A 10 mg/5 mg pre-mixed vial pairing tesamorelin, the GHRH analog with the strongest clinical evidence for visceral fat reduction, with ipamorelin as the ghrelin-receptor partner. The 2:1 ratio keeps tesamorelin as the primary driver while ipamorelin sharpens the GH pulse, making it the blend most often chosen for stubborn abdominal fat.
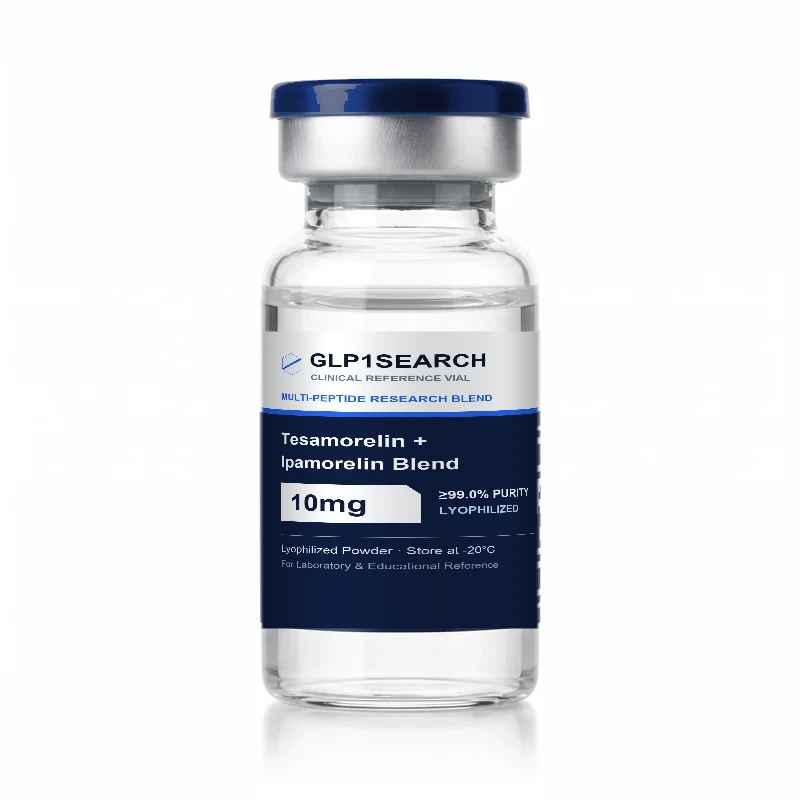 Tesamorelin + Ipamorelin Blend Reference Vial
Multi-Peptide Vial Composition
Select your vial strength to update all reference concentrations, dosage tables, and syringe draws on this page.
Arithmetic summary: Reconstituting a 15 mg Tesamorelin + Ipamorelin Blend vial with 2 mL of bacteriostatic water yields 7.5 mg/mL. Every 10 units (0.10 mL) on a U-100 insulin syringe delivers 750 mcg.
Tesamorelin + Ipamorelin Blend · 15 mg VialSelect a row to preview the draw on the syringe. Values are reference figures from the literature, not medical advice.
| Phase | Dose | mL | Units | Doses/Vial |
|---|---|---|---|---|
| BeginnerOnce nightly · Weeks 1–2 | 750 mcg (500 Tesa / 250 Ipa) | 0.10 | 10 | 20 |
| StandardOnce nightly · Weeks 3–4 | 1.5 mg (1 mg Tesa / 500 Ipa) | 0.20 | 20 | 10 |
| TargetOnce nightly · Weeks 5–8+ | 2.25 mg (1.5 mg Tesa / 750 Ipa) | 0.30 | 30 | 6 |
U-100 syringe drawn to 10 units (0.10 mL), 750 mcg (500 Tesa / 250 Ipa).
Dose exceeds this syringe's capacity. Choose a larger syringe or reduce the diluent volume.
Click any dosing tier row above to preview that exact draw on the U-100 syringe scale.
Four steps, in order. Work on a clean surface with washed hands and swab every vial top with alcohol first.
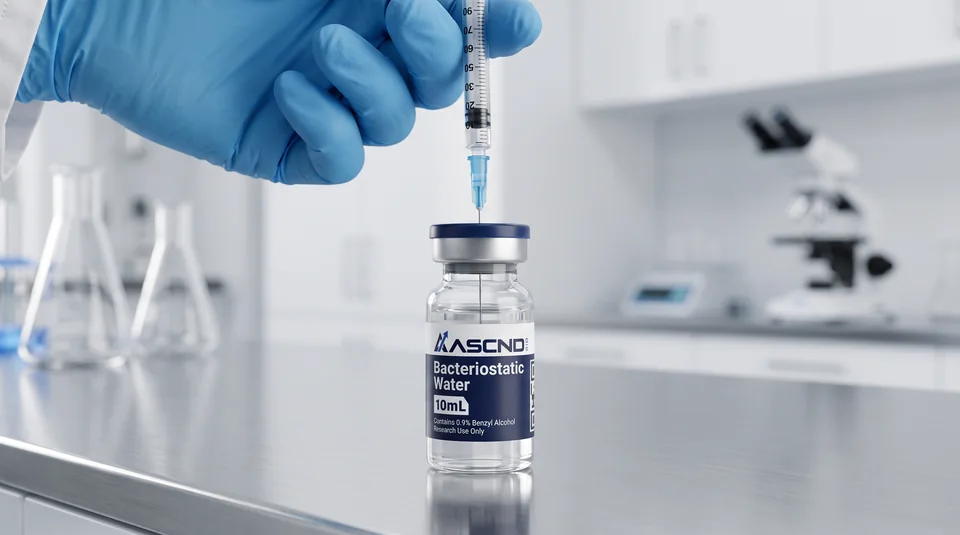 Step 01
Draw 2 mL of bacteriostatic water (0.9% benzyl alcohol) into a sterile syringe. Use bacteriostatic, not plain sterile water, so the multi-dose vial stays preserved between draws.
 Step 02
Pierce the stopper and angle the needle at 45° so the water runs slowly down the inside glass wall. Never spray directly onto the lyophilized puck: the jet foams the solution and can denature fragile peptide chains.
 Step 03
Roll the vial gently between your fingers or swirl in a slow circle until the liquid is 100% clear with no undissolved particles. Shaking shears peptide bonds and traps air bubbles; if it clouds, let it rest in the fridge for 15 minutes.
 Step 04
Write the reconstitution date and concentration on the vial. Refrigerate upright at 2–8 °C (36–46 °F), protected from light, and use within 28–30 days. Do not freeze the reconstituted liquid.
Convert a lyophilized peptide vial amount and bacteriostatic water volume into a reconstitution concentration, then translate your protocol dose and schedule into exact U-100 syringe units and multi-week vial supplies.
Enter the peptide amount in the vial and the volume of bacteriostatic or sterile water you plan to add.
Concentration
How much peptide each mL of solution contains after mixing.
5 mg/mL
Enter the dose from your protocol, select your dosing schedule, and pick the insulin syringe you are using.
100-unit (1 mL): marks every 2 units. Standard barrel for draws up to 100 units.
Draw to
Pull plunger seal to line 5
Volume
0.05 mL
Delivers 250 mcg
Doses per vial
20
Lasts 20 days (Once daily)
4-Week Schedule Supply
2 vials
28 doses · 2.0 mL BAC water
| Duration | Total Peptide | Vials Required | U-100 Syringes | BAC Water |
|---|
For educational and research calculations only. Always confirm calculations independently before use.
Plan vials, U-100 insulin syringes, bacteriostatic water, and sterile alcohol prep pads by protocol duration.
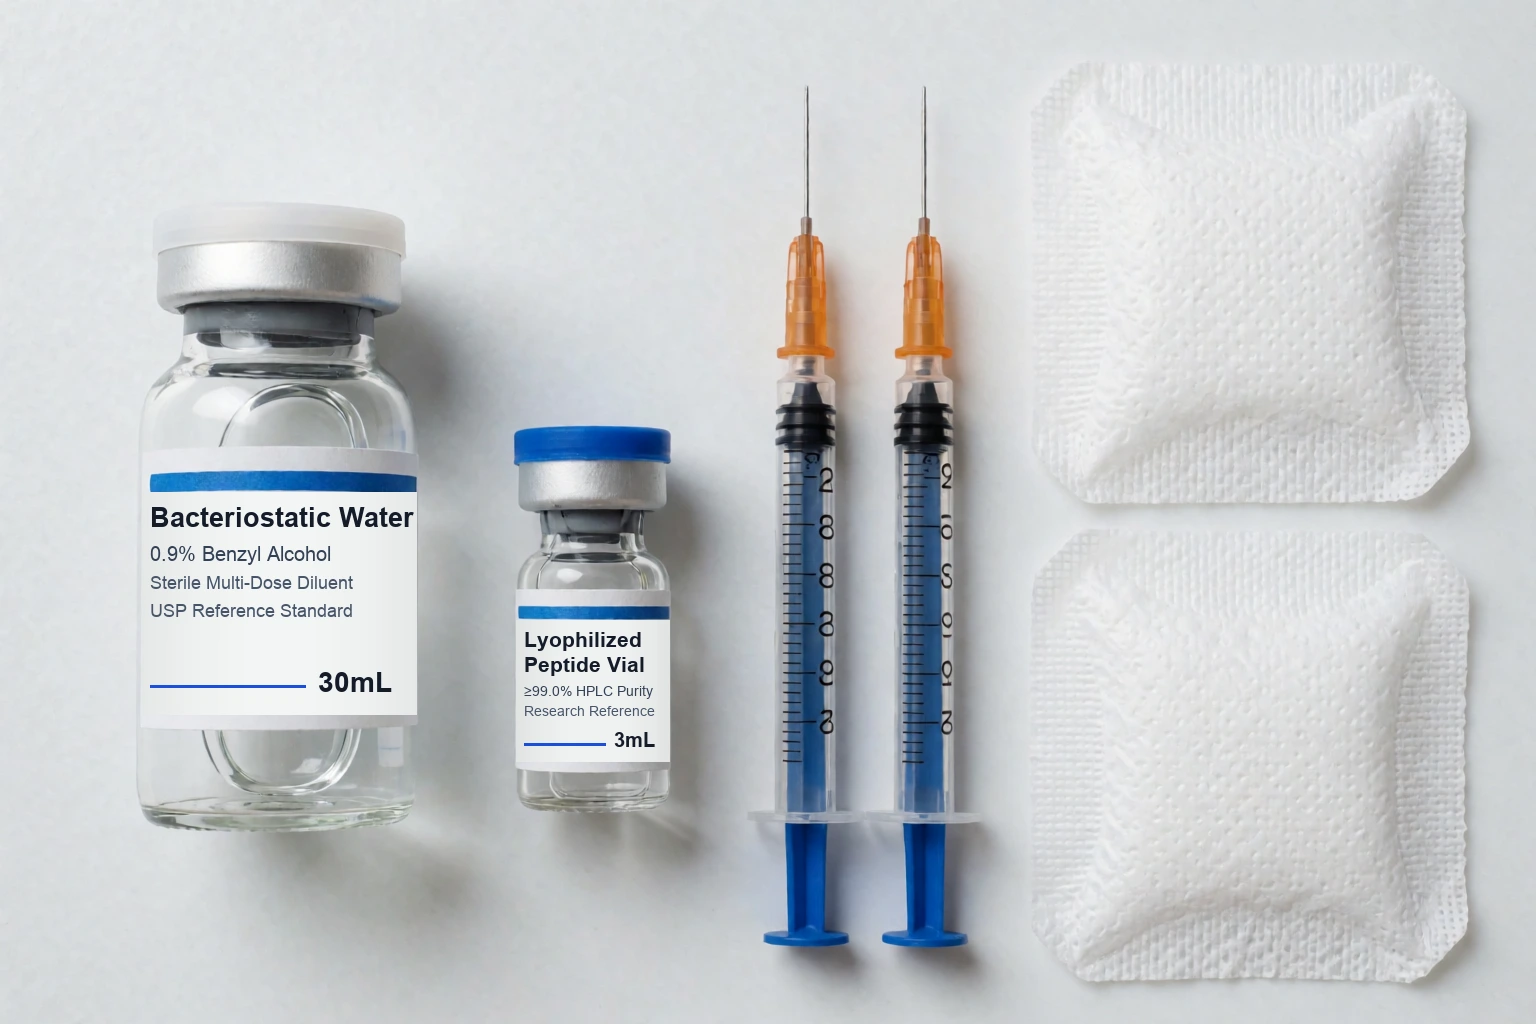
Tesamorelin + Ipamorelin Blend Vials (15 mg each):
U-100 Insulin Syringes & Alcohol Pads:
56 total doses over 8 weeks
84 total doses over 12 weeks
112 total doses over 16 weeks
Synergistic Protocols
Common research and clinical combinations pairing Tesamorelin + Ipamorelin Blend with complementary pathways.
Pairs a GHRH analog (amplifying pulse peak) with a selective ghrelin mimetic (initiating pulse release without cortisol or prolactin spikes).
| Compound | Protocol Dose | Timing & Route |
|---|---|---|
| CJC-1295 (No DAC) | 100–200 mcg per injection | Nightly before bed (90+ min fasted) |
| Ipamorelin | 100–200 mcg per injection | Co-administered nightly (optional AM fasted pulse) |
Stacking Note: Carbohydrates and dietary fats blunt GH release; administer at least 90–120 minutes after your final evening meal.
Combines FDA-studied GHRH analog Tesamorelin (selective trunk/visceral adipose lipolysis) with a nighttime Ipamorelin pulse.
| Compound | Protocol Dose | Timing & Route |
|---|---|---|
| Tesamorelin | 1.0–2.0 mg once daily | Morning fasted or pre-bed SubQ |
| Ipamorelin | 100–200 mcg once daily | Pre-bed fasted SubQ |
Stacking Note: Monitor fasting glucose and serum IGF-1 levels at baseline and week 8.
Systemic GH/IGF-1 elevation upregulates collagen synthesis while BPC-157 increases local growth hormone receptor expression on fibroblasts.
| Compound | Protocol Dose | Timing & Route |
|---|---|---|
| Sermorelin or CJC-1295/Ipamorelin | 200–300 mcg nightly | Pre-bed fasted SubQ |
| BPC-157 | 250–500 mcg daily | Morning or post-training SubQ |
Stacking Note: One of the most widely studied clinical combinations for post-surgical and athletic soft-tissue recovery.
Rotate sites with every injection so no single area is used twice in a row. Swab with alcohol and let it dry for 10 seconds before injecting.
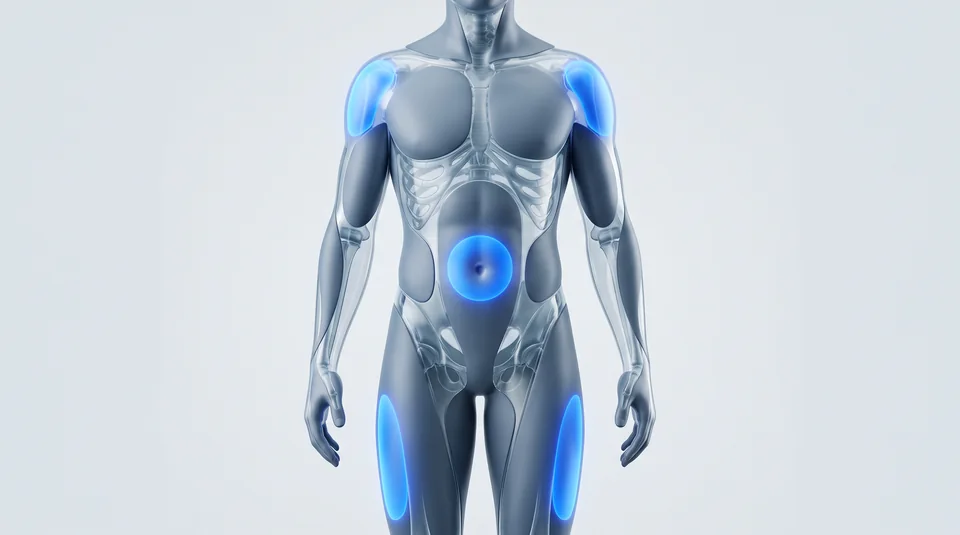
Zone 01
Abdomen
≥ 2 in away from navel
Zone 02
Outer Thigh
Middle third, anterior-lateral
Zone 03
Upper Arm
Posterior / outer tricep pad
90° · 4–8 mm (31 G) short needle
Standard U-100 insulin syringe: pinch a light fold and insert straight in at 90°.
45° · 12.7 mm (1/2 in) needle
Longer needle or leaner area: pinch a 1-inch fold and enter at 45° into fat.
Aseptic Injection Checklist
• Use a brand-new sterile U-100 syringe for every draw (never reuse needles).
• Swab both the vial rubber stopper and injection site with 70% isopropyl alcohol and let dry.
• Rotate clockwise around the abdomen or alternate left/right thigh to prevent lipohypertrophy.
Lyophilized Powder (Unmixed)
Freezer −20 °C Long-Term · Fridge Short-Term
Unmixed freeze-dried vials stay stable for months in the refrigerator and 1–2+ years at −20 °C (0 °F) in the dark. Let the vial warm to room temperature before opening.
Reconstituted Liquid (Mixed)
Refrigerate 2–8 °C (36–46 °F) · Use Within 30 Days
Keep refrigerated and out of light once mixed with bacteriostatic water. Never freeze reconstituted liquid — ice crystals shear the dissolved peptide chains.
Pharmacology & Evidence
How It Works
Tesamorelin is a stabilized GHRH(1-44) analog that increases GH pulse amplitude and downstream IGF-1 and has been shown to reduce visceral adipose tissue in controlled trials. Ipamorelin activates GHS-R1a to trigger the pulse and inhibit somatostatin, producing a GHRH + GHRP synergy similar to CJC/ipamorelin but with the longer-acting and clinically dosed tesamorelin as the GHRH component.
subcutaneous
750mcg-1.5mg · Daily at bedtime
8-12 weeks
subcutaneous
1.5-2.25mg · Daily at bedtime
12-26 weeks
Research use only. Not medical advice.
Tesamorelin 2 mg daily reduced visceral adipose tissue by ~15% over 26 weeks versus placebo in HIV lipodystrophy
Twenty weeks of tesamorelin improved executive function in healthy older adults and those with mild cognitive impairment
Research compound; not FDA-approved. Tesamorelin alone is approved (Egrifta) for HIV-associated lipodystrophy; the blend with ipamorelin has no approved indication.
Clinical Profile
Provider Directory
Pre-mixed 15 mg vials are sold by research vendors; verify both peptides are listed on the COA with the 2:1 ratio. Tesamorelin is relatively unstable once reconstituted — use within 2-3 weeks refrigerated.
Free Guide
New studies, regulatory changes and sourcing notes on the peptides you follow. One email a week, no spam.
Free. No spam. Unsubscribe anytime. From GLP1Search.
Use location pages to compare clinics with peptide therapy signals and verify clinical oversight before treatment.